
Total Knee Replacement Surgery in Egypt
Walking without pain again after advanced knee arthritis
Replacing the damaged knee joint with a long-lasting implant, using a technique that preserves as much healthy tissue as possible, with a rehabilitation protocol that starts on day one after surgery.
When does knee replacement become the right option?
Joint replacement is not the first step in treating knee arthritis — it is the last, after conservative treatment has failed. Surgery is usually considered when there is:
- Grade 3 or 4 arthritis confirmed on X-ray
- Persistent pain unresponsive to medication, physiotherapy and injections
- Pain at rest or night pain that prevents sleep
- Severe restriction of movement affecting stairs and daily activity
- Visible deformity of the leg axis (varus or valgus)
- Declining ability to walk even short distances, or reliance on a stick
Don’t rush the decision: in early or moderate arthritis, non-surgical measures — weight loss, quadriceps strengthening, and injections — often help and can delay surgery for years. In younger patients with a deformed leg axis, an osteotomy may preserve the natural joint instead.
Types of intervention by joint condition
Not every knee needs a total replacement. The type of intervention is determined after clinical examination and imaging that establish which compartments are actually damaged.
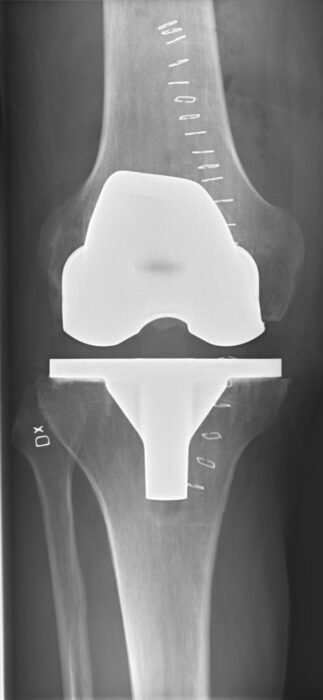
Total knee replacement
Resurfacing all three compartments when the whole joint is affected — the most common option in advanced arthritis.
Partial (unicompartmental) replacement
Replacing only the damaged compartment when arthritis is confined to one side, through a smaller incision with faster recovery.
Osteotomy (axis correction)
Redistributing load onto the healthy compartment in younger patients with deformity, preserving the natural joint.
Implant types
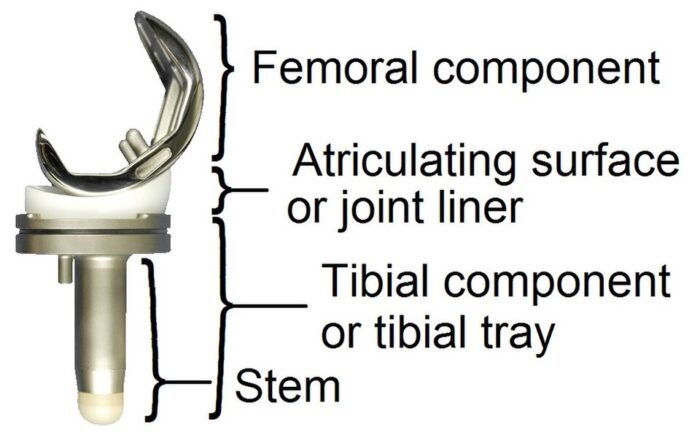
Implants differ in material, design and expected lifespan; the choice follows age, activity level and bone quality.
Revision surgery
Replacing a previous implant after loosening, infection or wear — a more complex operation requiring specific experience.
Bilateral knee replacement
Both knees in one session or staged, decided by cardiac and respiratory status and the patient’s general fitness.
Types of knee replacement surgery performed by Prof. Dr. Ibrahim Shaarawi
Alongside total knee replacement, Prof. Dr. Ibrahim Shaarawi performs four other operations for knee arthritis. The right one is chosen after examination and imaging, based on which part of the joint is damaged and on the patient’s age, activity and general health.
Partial (unicompartmental) knee replacement
Only the damaged part of the joint, usually the inner side, is replaced, while the rest of the joint and the healthy ligaments are kept.
- Suits: arthritis confined to one side of the knee, with intact ligaments and good movement.
- Advantages: a smaller incision, usually a quicker recovery, and a knee that feels more natural.
- Not suitable for: arthritis across several compartments, severe deformity, or rheumatoid arthritis.
Read more about partial knee replacement.
Both knees in one operation
When both knees have advanced arthritis, both joints can be replaced in the same operation instead of two separate ones.
- Advantages: one anaesthetic, one hospital stay and one rehabilitation period for both knees.
- Requirement: good heart and lung fitness, confirmed by a full medical assessment before surgery.
- Alternative: staged surgery, one knee at a time, when general health does not allow both together.
See when you need a knee replacement.
Revision knee replacement
Replacing a previous artificial knee that no longer works well. It is more complex than the first operation and needs special implants and instruments.
- Causes: loosening, infection around the implant, instability, wear, or a fracture around the implant.
- Assessment: serial X-rays and inflammatory blood tests, sometimes joint fluid sampling, before the plan is set.
- Infection: treatment sometimes needs surgery in two stages.
Read more about failed knee replacement and revision surgery.
High tibial osteotomy (knee realignment)
An option that keeps the patient’s own joint: the leg axis is corrected to shift load from the worn part of the knee to the healthy part, and the bone is fixed with a plate.
- Suits: younger, active patients with bow legs and arthritis on the inner side only.
- Advantages: preserves the natural joint and may delay the need for a replacement.
- Not suitable for: advanced arthritis throughout the knee.
See alternatives to knee replacement.
| Operation | Who is it for? | What is replaced or corrected? |
|---|---|---|
| Total knee replacement | Advanced arthritis throughout the joint | All joint surfaces |
| Partial knee replacement | Arthritis on one side with intact ligaments | Only the damaged part |
| Both knees together | Advanced arthritis in both knees with good general fitness | Both joints in one operation |
| Revision | Failure of a previous artificial knee | The old implant, with a dedicated revision implant |
| High tibial osteotomy | Younger active patients with bow legs and one-sided arthritis | The leg axis, keeping the natural joint |
Video: Types of artificial knee joints for the different grades of knee arthritis
Prof. Dr. Ibrahim Shaarawi, Professor of Orthopaedic Surgery, explains (in Arabic).
Your treatment pathway, step by step
Assessment and imaging
Clinical examination of range of movement, stability and leg axis, with plain knee X-rays and long-leg views to establish the grade of arthritis and any deformity.
Exhausting conservative treatment
Weight loss, a quadriceps strengthening programme, anti-inflammatory medication and injections where indicated — with the response assessed before surgery is offered.
Pre-operative preparation
Full blood work, cardiac and respiratory assessment, and control of diabetes and blood pressure, with blood thinners stopped for a period determined by your doctor.
The operation
Removing the worn surfaces and implanting the prosthesis with precise alignment of the leg axis and ligament balancing, under spinal or general anaesthesia as the anaesthetist advises.
Early mobilisation
Standing and assisted walking usually begin within the first 24 hours, with a pain control protocol and thromboprophylaxis.
Rehabilitation and follow-up
A graded physiotherapy programme to restore range of movement and muscle strength, with periodic imaging to confirm the implant remains stable.
What determines a good outcome?
The result of a knee replacement depends on more than the operation itself — it starts before theatre and continues for months afterwards.
- Accurate alignment and ligament balanceThe single biggest factor in comfort and implant longevity; a small alignment error translates into pain and early wear.
- Choosing the right implantDesign and material are selected by age, activity level and bone quality — not by price alone.
- Commitment to physiotherapyThe range of movement achieved in the first six weeks is usually what the knee settles at long term.
- Control of chronic diseaseUncontrolled diabetes and obesity raise the risk of wound infection and affect the final result.
- ThromboprophylaxisA combined medical and mobility protocol from day one to reduce the risk of deep vein thrombosis.
- Long-term follow-upPeriodic imaging detects loosening or wear early, before it becomes a problem requiring revision surgery.
Why Prof. Dr. Ibrahim Shaarawi
Looking for an experienced knee surgeon? Read our guides to the best knee specialist in Egypt and the best orthopaedic surgeon in Egypt to see how to choose.
- Assessment before any decision to operateSurgery is offered only after appropriate conservative treatment has been exhausted, because many patients improve without an operation.
- Academic backgroundMD and MSc in Orthopedic Surgery from Ain Shams University, with training in the Ain Shams University hospitals.
- International trainingVisiting professor and training at Ohio State University Hospital in the United States, applying the protocols used there.
- One plan from diagnosis to rehabilitationDiagnosis, surgery, physiotherapy and follow-up handled as a single pathway rather than split across separate providers.
Read patient success stories or review the full profile and credentials.
Cost and booking
The cost of knee replacement varies considerably with the implant used and where it is manufactured, whether the replacement is total or partial, how many knees are being treated, the hospital and length of stay, and the type of anaesthesia.
Knee replacement with Prof. Dr. Ibrahim Shaarawi typically costs EGP 120,000–200,000, varying within that range with the implant, the hospital and whether one or both knees are replaced. Revision and complex cases are priced after assessment. See knee replacement cost in Egypt for details.
For that reason no final figure is quoted before examination and imaging. After assessment you receive a clear plan naming the proposed implant and its itemised cost before any decision is made.
Important: bring all previous imaging and reports to your first visit, along with a list of your current medications, so an accurate plan can be made from the outset.
Frequently asked questions
How long does a knee implant last?
This varies with the implant type, the patient’s weight and activity level, and the quality of the implantation. Maintaining a healthy weight and avoiding high-impact sport measurably extends implant life, while obesity and vigorous activity accelerate wear.
When will I walk after surgery?
In most cases standing and assisted walking begin within the first 24 hours. How quickly you come off a frame or stick varies with age, muscle strength and commitment to physiotherapy.
Is the operation painful?
Post-operative pain is expected but managed with a multimodal protocol that begins during surgery itself. Most patients describe it as less severe and shorter-lived than the chronic arthritic pain they had before.
Can both knees be replaced at the same time?
It is possible in selected patients, and the decision depends on cardiac and respiratory status, haemoglobin level and general fitness. Doing both together shortens total rehabilitation but places a greater load on the body, and is discussed case by case.
What are the risks and complications?
As with any major surgery there is a risk of infection, thrombosis, joint stiffness, or loosening of the implant over time. These are uncommon and are reduced considerably by good preparation, control of chronic disease, and adherence to the post-operative protocol.
Will I be able to kneel afterwards?
Most patients regain a range of movement that allows comfortable daily activity, and many return to kneeling to varying degrees. Full squatting or sitting cross-legged remains difficult for some patients and depends on the range achieved through physiotherapy.
Book a knee assessment
If you have chronic knee pain, or have been told you need a joint replacement, the right next step is an assessment that establishes whether you are genuinely a candidate for surgery or whether a better option exists.
Your complete knee replacement guide
Detailed guides written and reviewed by Prof. Dr. Ibrahim Shaarawi for every stage, from the decision to recovery:
The decision: do I need a new knee?
Cost, implants and the operation
Results and risks
Recovery and life after surgery
Related reading
References
- American Academy of Orthopaedic Surgeons (AAOS) — Patient guidelines
- Mayo Clinic — Orthopedic procedures
- NICE — Joint replacement and arthroscopy guidance
- Cochrane Musculoskeletal reviews
- Evans JT, et al. How long does a knee replacement last? A systematic review and meta-analysis of case series and national registry reports with more than 15 years of follow-up. Lancet. 2019;393(10172):655-663.
- American Academy of Orthopaedic Surgeons (OrthoInfo). Total Knee Replacement.
Medical disclaimer: the content on this page is provided for medical education only. It is not a substitute for consultation and clinical examination, and must not be used as a basis for self-diagnosis or self-treatment. Read the full medical disclaimer.