
Quick answer
A bone density test (DEXA) is a quick, safe low-dose X-ray that measures bone density at the lumbar spine and hip. The key result is the T-score: −1 or higher is normal, between −1 and −2.5 is low bone mass (osteopenia), and −2.5 or lower is osteoporosis. It is recommended for women from 65 and men from 70, and earlier with risk factors or after a fracture from a minor fall.
✅ Last medically reviewed by Prof. Dr. Ibrahim Shaarawi, Professor of Orthopaedic Surgery, on 5 October 2026
Many patients bring a DEXA report full of numbers they do not understand, and some worry needlessly about a negative value. This article explains how to read the result and what comes next, as part of our guide to osteoporosis.
What is a DEXA scan?
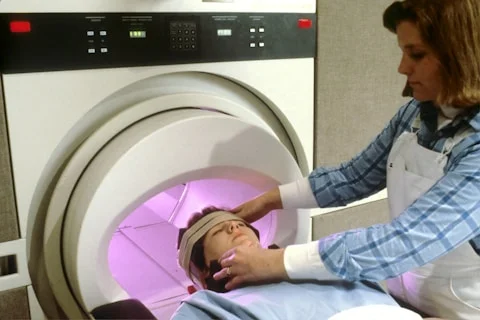
Dual-energy X-ray absorptiometry (DXA or DEXA) uses a very low dose of X-rays. You lie on the table for 10–20 minutes with no pain or injections while the scanner measures the mineral content of bone, usually at the lumbar spine and hip (total hip and femoral neck), sometimes the forearm. The radiation dose is lower than a standard chest X-ray.
How to read your result: the T-score
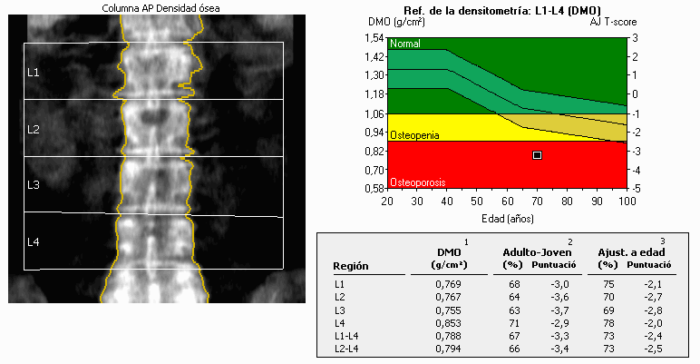
The T-score compares your bone density with that of a healthy young adult of the same sex, expressed in standard deviations. It is used for women after menopause and men over 50, under the WHO classification:
| T-score | Interpretation | What it means for you |
|---|---|---|
| −1 or higher | Normal | Keep up diet, exercise and vitamin D |
| Between −1 and −2.5 | Low bone mass (osteopenia) | Assess risk factors; may need treatment if fracture risk is high |
| −2.5 or lower | Osteoporosis | Usually needs medication |
| −2.5 or lower with a fragility fracture | Severe (established) osteoporosis | Prompt treatment, possibly a bone-building drug |
Example: a T-score of −1.8 means low bone mass, not osteoporosis; −2.7 means osteoporosis. The lowest value among spine and hip sites determines the diagnosis.
Video: preventing fractures after 50
What is a Z-score?
The Z-score compares your bone density with people of your own age and sex. It is used for premenopausal women, men under 50 and children. A Z-score of −2 or lower is “below the expected range for age” and calls for a search for secondary causes such as osteomalacia, endocrine disorders, malabsorption or medicines.
Who needs a bone density test?
- Women aged 65 or older and men aged 70 or older.
- Postmenopausal women and men aged 50–69 with risk factors: low weight, smoking, a parent with a hip fracture, early menopause.
- Anyone with a fracture after a minor fall after age 50 (wrist, spine, hip, shoulder).
- Oral steroid use for 3 months or more.
- Conditions such as rheumatoid arthritis, hyperparathyroidism, malabsorption, and after bariatric surgery.
- Before and during treatment with bone-weakening drugs such as some breast and prostate cancer therapies.
- Monitoring osteoporosis treatment.
For women specifically, see osteoporosis symptoms in women.
How to prepare
- Stop calcium tablets 24 hours before the scan.
- Tell the staff about any contrast, barium or nuclear medicine test in the previous two weeks.
- Tell the doctor if you might be pregnant.
- Wear comfortable clothes without metal.
- Have follow-up scans on the same machine and at the same centre when possible.
Limitations: when the result can mislead
- Spinal arthritis and bone spurs in older people can falsely raise spine readings, so we rely more on the hip.
- Old vertebral fractures or metal implants in the measured area.
- Osteomalacia gives low density that mimics osteoporosis, so we check vitamin D and alkaline phosphatase before starting osteoporosis drugs.
- Density alone does not capture all fracture risk; we combine it with age, previous fractures and risk factors in the FRAX calculator.
Key numbers to know
- In the FREEDOM trial, Prolia cut new vertebral fractures by 68% (2.3% vs 7.2%) and hip fractures by 40% (Cummings et al., NEJM 2009).
- In the HORIZON trial, yearly zoledronic acid cut vertebral fractures by 70% and hip fractures by 41% over 3 years (Black et al., NEJM 2007).
- Calcium supplements lowered overall fracture risk by about 11% in randomised trials but did not reduce hip fractures (Bolland et al., BMJ 2015).
| Treatment | When we use it | Notes |
|---|---|---|
| Calcium, vitamin D, exercise and fall prevention | Everyone with or at risk of osteoporosis | The foundation, but not enough alone in established osteoporosis |
| Bisphosphonate tablets | Osteoporosis without multiple fractures | Taken correctly on an empty stomach |
| Zoledronic acid (yearly infusion) | People preferring a yearly dose with good kidney function | Cut vertebral fractures by 70% in HORIZON |
| Prolia injection every 6 months | High fracture risk or moderate kidney disease | Must not be stopped abruptly without a follow-on drug |
| Bone-building drugs (teriparatide or romosozumab) | Severe osteoporosis and multiple fractures | Followed by a maintenance drug after the course |
| Fracture surgery (fixation or replacement) | When a hip or other fracture occurs | Together with starting osteoporosis treatment to prevent the next fracture |
At Prof. Dr. Ibrahim Shaarawi’s clinics in Nasr City, Mohandeseen and New Cairo (5th Settlement) we review your vitamin D, calcium and bone density results and examine the cause of pain or fracture before deciding on the right dose or osteoporosis treatment.
What happens after the result?
| Result | Usual next step |
|---|---|
| Normal | Adequate vitamin D, dietary calcium, exercise, repeat scan depending on risk |
| Osteopenia | FRAX risk calculation, treat causes, medication if risk is high |
| Osteoporosis | Baseline tests, then treatment such as bisphosphonates, the 6-monthly Prolia injection or zoledronic acid |
| Osteoporosis with fractures | Potent, possibly bone-building treatment and fall prevention |
During treatment we usually repeat the scan every one to two years on the same machine. Treatment options are in osteoporosis and the role of vitamin D in vitamin D and fractures in older adults.
Frequently asked questions about the bone density test
What is a normal bone density result?
A T-score of −1 or higher is normal. Between −1 and −2.5 means low bone mass (osteopenia), and −2.5 or lower means osteoporosis.
What is the difference between a T-score and a Z-score?
The T-score compares you with a healthy young adult and is used after menopause and in men over 50; the Z-score compares you with people your age and is used in younger adults and children.
Does a DEXA scan involve harmful radiation?
The dose is very low — less than a standard chest X-ray — and the test is safe, painless and takes 10–20 minutes.
How often should a bone density test be repeated?
Usually every one to two years during osteoporosis treatment; if normal, the interval depends on your risk factors. Use the same machine when possible.
Does osteopenia need treatment?
Not always. It depends on fracture risk calculated from age, previous fractures and risk factors; many people need only vitamin D, calcium and exercise, and some need medication.
To have your bones assessed and your tests reviewed, book a consultation, call +20 155 240 4488 or message us on WhatsApp at +20 155 554 7181.
Medically reviewed by Prof. Dr. Ibrahim Shaarawi, Professor of Orthopaedic Surgery. This article is general medical education and does not replace an examination or the treatment plan your doctor sets for you. See our medical disclaimer.
Related vitamin D and bone health guides
Related guides on bone density and osteoporosis:
- Osteoporosis
- The 6-monthly osteoporosis injection (Prolia)
- Osteoporosis symptoms in women
- Vitamin D and fractures in older adults
- Preventing falls and fractures in older adults
- Femoral neck fracture in older adults
- Vitamin D deficiency
- Osteomalacia
- Calcium injections for bones
References
- Kanis JA, et al. European guidance for the diagnosis and management of osteoporosis in postmenopausal women. Osteoporos Int. 2019;30(1):3-44.
- Camacho PM, et al. AACE/ACE Clinical Practice Guidelines for the Diagnosis and Treatment of Postmenopausal Osteoporosis — 2020 Update. Endocr Pract. 2020;26(Suppl 1):1-46.
- Shuhart CR, et al. Executive Summary of the 2019 ISCD Position Development Conference on Monitoring Treatment, DXA Cross-calibration and Least Significant Change. J Clin Densitom. 2019;22(4):453-471.
- American Academy of Orthopaedic Surgeons (OrthoInfo). Osteoporosis.