
Quick answer
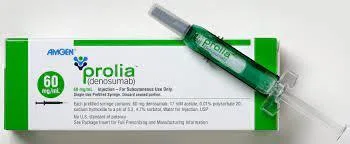
The osteoporosis injection every 6 months is Prolia (denosumab 60 mg) given under the skin. It switches off bone-resorbing cells and, in the FREEDOM trial, cut new vertebral fractures by about 68% and hip fractures by about 40%. Its effect on bone breakdown starts within days; density gains show within months. Before the injection, vitamin D and calcium must be corrected and dental health reviewed, and it must not be stopped or delayed without a follow-on plan.
✅ Last medically reviewed by Prof. Dr. Ibrahim Shaarawi, Professor of Orthopaedic Surgery, on 5 October 2026
This injection is one of the most effective osteoporosis treatments I prescribe, but it is also the one where patient education matters most — particularly about timing and stopping. Here is what you need to know, as part of our guide to osteoporosis.
How does Prolia work?
Denosumab is an antibody that blocks RANKL, the signal that activates osteoclasts — the cells that break bone down. With bone breakdown suppressed, bone density rises and fracture risk falls. It is injected under the skin of the arm, thigh or abdomen once every 6 months.
Tests and preparation before the injection
- Vitamin D and calcium: deficiency increases the risk of low calcium after Prolia, so we correct it first — see vitamin D deficiency and vitamin D injections.
- Kidney function: patients with kidney disease are more prone to low calcium.
- Dental check and completion of major dental work if possible, because of a rare risk of jaw osteonecrosis.
- A bone density (DEXA) scan to confirm the diagnosis and record a baseline.
Key numbers to know
- In the FREEDOM trial, Prolia cut new vertebral fractures by 68% (2.3% vs 7.2%) and hip fractures by 40% (Cummings et al., NEJM 2009).
- In the HORIZON trial, yearly zoledronic acid cut vertebral fractures by 70% and hip fractures by 41% over 3 years (Black et al., NEJM 2007).
- Calcium supplements lowered overall fracture risk by about 11% in randomised trials but did not reduce hip fractures (Bolland et al., BMJ 2015).
At Prof. Dr. Ibrahim Shaarawi’s clinics in Nasr City, Mohandeseen and New Cairo (5th Settlement) we review your vitamin D, calcium and bone density results and examine the cause of pain or fracture before deciding on the right dose or osteoporosis treatment.
Video: taking calcium but your bones are still weak?
When does the osteoporosis injection start working?
Bone breakdown falls within days of the injection, bone density gains are usually visible on a scan after 6–12 months, and fracture risk falls with continued treatment. We usually repeat the DEXA scan after one to two years.
Side effects
| Side effect | How common | What to do |
|---|---|---|
| Back, muscle or joint pain | Common and mild | Simple pain relief |
| Low calcium | More likely with vitamin D deficiency or kidney disease | Correct vitamin D and calcium beforehand and monitor |
| Skin infection (cellulitis) | Uncommon | See a doctor for red, hot skin |
| Jaw osteonecrosis | Very rare | Good dental care; tell your dentist about the treatment |
| Atypical thigh-bone fracture | Very rare with long-term use | Report new thigh or groin pain promptly |
| Multiple spinal fractures after abrupt stopping | When stopped without a follow-on drug | Do not delay a dose by more than 4 weeks |
What happens if you stop or delay Prolia?
Prolia’s effect wears off about 6 months after each dose. If the next dose is missed, bone breakdown rebounds and the density gained can be lost quickly. An analysis of the FREEDOM trial found a higher risk of multiple vertebral fractures in people who stopped without another treatment. Therefore:
- Keep to the 6-monthly schedule and do not be more than 4 weeks late.
- If stopping is planned, your doctor will switch you to a bisphosphonate such as zoledronic acid.
- Do not stop because your density improved or because of cost without discussing it first.
Prolia vs zoledronic acid vs teriparatide
| Prolia | Zoledronic acid | Teriparatide | |
|---|---|---|---|
| Given as | Injection under the skin every 6 months | Yearly intravenous infusion | Daily injection under the skin |
| Action | Stops bone breakdown | Reduces bone breakdown | Builds new bone |
| On stopping | Needs a follow-on drug | Effect persists in bone for a long time | Followed by a maintenance drug |
| Often suits | High fracture risk, moderate kidney disease | Those preferring a yearly dose with good kidneys | Severe osteoporosis, multiple fractures |
Prices change frequently in Egypt; we confirm the current cost at your consultation. For the evidence on vitamin D and fractures see vitamin D and fractures in older adults.
Frequently asked questions about the 6-monthly osteoporosis injection
What is the osteoporosis injection every 6 months called?
It is Prolia, containing denosumab 60 mg, given under the skin once every 6 months.
When does the osteoporosis injection start working?
It reduces bone breakdown within days; density gains appear on a scan after 6–12 months of continued treatment.
What are the side effects of the osteoporosis injection?
Mostly back and muscle pain and low calcium, especially with vitamin D deficiency; rarely skin infection, jaw osteonecrosis or an atypical thigh fracture. The biggest risk comes from stopping it abruptly.
Should I take vitamin D before Prolia?
Yes. Vitamin D and calcium deficiency must be corrected before the injection and monitored, because deficiency increases the risk of low calcium.
What if I am late for my Prolia dose?
Being more than a few weeks late lets bone breakdown rebound; stopping without a follow-on drug raises the risk of multiple spinal fractures.
What is the difference between the 6-monthly and the monthly osteoporosis injection?
The 6-monthly injection is Prolia, which stops bone breakdown. The so-called monthly injection is a teriparatide pen injected daily for a month, which builds new bone.
To have your bones assessed and your tests reviewed, book a consultation, call +20 155 240 4488 or message us on WhatsApp at +20 155 554 7181.
Medically reviewed by Prof. Dr. Ibrahim Shaarawi, Professor of Orthopaedic Surgery. This article is general medical education and does not replace an examination or the treatment plan your doctor sets for you. See our medical disclaimer.
Related vitamin D and bone health guides
Related guides in our osteoporosis series:
- Osteoporosis
- Osteoporosis symptoms in women
- The bone density (DEXA) test
- Vitamin D and fractures in older adults
- Preventing falls and fractures in older adults
- Femoral neck fracture in older adults
- Vitamin D deficiency
- Vitamin D injections
- Calcium injections for bones
References
- Cummings SR, et al. Denosumab for prevention of fractures in postmenopausal women with osteoporosis. N Engl J Med. 2009;361(8):756-65.
- Cummings SR, et al. Vertebral Fractures After Discontinuation of Denosumab: A Post Hoc Analysis of the FREEDOM Trial and Its Extension. J Bone Miner Res. 2018;33(2):190-198.
- Tsourdi E, et al. Discontinuation of Denosumab therapy for osteoporosis: A systematic review and position statement by ECTS. Bone. 2017;105:11-17.
- Black DM, et al. Once-yearly zoledronic acid for treatment of postmenopausal osteoporosis. N Engl J Med. 2007;356(18):1809-22.
- Neer RM, et al. Effect of parathyroid hormone (1-34) on fractures and bone mineral density in postmenopausal women with osteoporosis. N Engl J Med. 2001;344(19):1434-41.
- Khan AA, et al. Diagnosis and management of osteonecrosis of the jaw: a systematic review and international consensus. J Bone Miner Res. 2015;30(1):3-23.
- Camacho PM, et al. AACE/ACE Clinical Practice Guidelines for the Diagnosis and Treatment of Postmenopausal Osteoporosis — 2020 Update. Endocr Pract. 2020;26(Suppl 1):1-46.
- Kanis JA, et al. European guidance for the diagnosis and management of osteoporosis in postmenopausal women. Osteoporos Int. 2019;30(1):3-44.