
What Does a Lipoma Look Like? lipoma can appear in various shapes and sizes, usually presenting as a soft, mobile lump beneath the skin in areas such as the shoulder, hand, leg, neck, or back. It typically takes a round or oval form and may feel soft or rubbery to the touch.
Appearance by site
In the hand and fingers, lipomas are usually small and harder to detect — they appear as subtle subcutaneous nodules. In the neck, back, and leg they tend to be larger and more visible. The key distinguishing feature of a benign lipoma is its soft, non-tender, freely mobile texture — which sets it apart from an abscess, ganglion cyst, or malignant tumour.
Visual Characteristics of Lipoma by Location
| Location | Common Appearance | Typical Size | Texture on Palpation | Ease of Detection | Recommended Specialty |
|---|---|---|---|---|---|
| Hand and fingers | Small round nodule beneath skin | 0.5–2 cm | Soft and mobile | Difficult — small size | Orthopaedic oncology |
| Neck and shoulder | Oval bulge visible beneath skin | 2–6 cm | Soft and rubbery | Easy — visible to eye | Dermatology / Orthopaedic oncology |
| Back and trunk | Flat or rounded mass | 2–10 cm | Pliable, non-tender | Moderate–easy | Dermatology / Orthopaedic oncology |
| Thigh and leg | Deep swelling — may not be visible | 3–10+ cm | Relatively firm — deep | Difficult — MRI required | Orthopaedic oncology (urgent) |
| Inflamed / complicated | Redness + swelling + warmth | Variable | Tender — tense | Very obvious | Urgent medical evaluation |
| * Visual features alone are insufficient for diagnosis. Any lipoma in the leg, hand, or shoulder exceeding 3 cm requires orthopaedic oncology evaluation and MRI. | |||||

Causes and Risk Factors
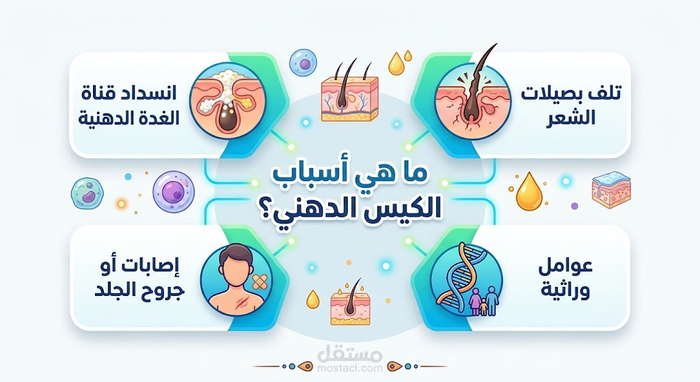
A lipoma forms when fat cells proliferate in an uncontrolled but benign manner beneath the skin. In most cases no single identifiable cause is found. Known contributing factors include:
| Factor | Mechanism | Modifiable? | Evidence Level | Recommended Action |
|---|---|---|---|---|
| Genetic predisposition | Gene mutations affecting adipocyte growth regulation | No | High | Early screening if family history present |
| Uncontrolled fat-cell division | Benign clonal proliferation of mature adipocytes | No | High | Regular monitoring of lump size |
| Repeated local trauma | Repeated injury may trigger adipocyte proliferation | Yes | Moderate | Avoid repeated blows to the same area |
| Rare hereditary syndromes (Familial Multiple Lipomatosis, Madelung) | Specific mutations causing multiple lipomas | No | Very high | Specialist referral + genetic testing if suspected |
| Age over 40 | Accumulation of DNA changes in adipocytes over time | No | High | Heightened vigilance for any new lump after age 40 |
| Idiopathic (unknown) | No identified cause — most common scenario | — | Variable | Manage based on size, location, and patient age |
| * Based on Mayo Clinic and UpToDate Lipoma Aetiology 2024. Treatment decisions are guided by lesion characteristics, not aetiology. | ||||
Is a Lipoma Dangerous?
Most lipomas are benign and pose no health risk. However, complications can arise if left unmanaged. Inflammation — triggered by repeated friction or trauma — can cause swelling and pain, and an infected lipoma may require antibiotics or surgical drainage. In rare cases, a lump that looks like a lipoma may instead be a liposarcoma — a malignant fatty-tissue tumour. This is why monitoring any change in shape, size, or texture is essential.
When Is a Lipoma Dangerous?
A lipoma requires urgent specialist evaluation when any of the following are present: size over 3 cm; patient age over 40 with a new or growing lump; deep location (adjacent to muscle or bone); location in the leg or hand; or rapid increase in size over weeks. These features raise concern for liposarcoma and mandate immediate surgical oncology assessment.
🔴 Critical Warning: Liposarcoma can be clinically indistinguishable from a benign lipoma — especially in the thigh and leg. MRI and biopsy are the only way to confirm the diagnosis. Never attempt to remove, drain, or massage a deep, large, or rapidly growing lump before specialist imaging.
Danger Criteria — Rapid Assessment Table
| Criterion | Typical Benign Lipoma | Suspicious for Malignancy | Priority | Action |
|---|---|---|---|---|
| Size | < 3 cm | > 5 cm or rapidly enlarging | Urgent | MRI + orthopaedic oncology referral |
| Depth | Superficial — directly under skin | Deep — adjacent to muscle / bone | Urgent | MRI mandatory before any intervention |
| Location | Back, neck, trunk | Thigh, leg, hand, deep shoulder | Urgent | Orthopaedic oncology specialist |
| Growth rate | Slow — months to years | Rapid — weeks | Very urgent | Immediate evaluation + imaging + biopsy |
| Texture | Soft, mobile, compressible | Firm, fixed, non-mobile | Urgent | Biopsy after imaging |
| Patient age | Under 40 | Over 40 with any above feature | Within one week | Orthopaedic oncology assessment |
| * Based on Mayo Clinic, ESSO, and AAOS guidelines. Physical examination alone cannot differentiate a benign lipoma from liposarcoma. | ||||
Symptoms
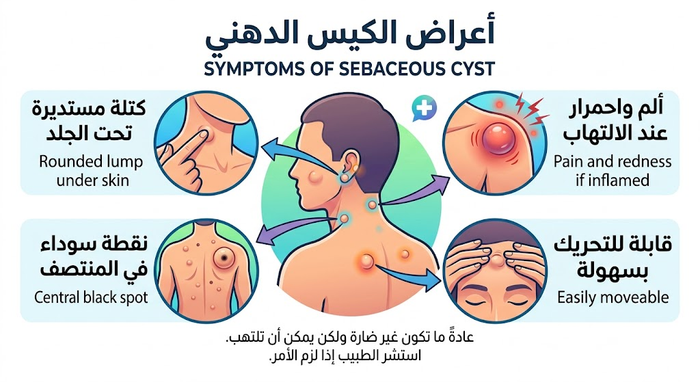
Common symptoms of a lipoma include: a small soft lump under the skin, mobile on palpation; usually painless, though it may cause discomfort if pressing on a tendon or nerve; redness and warmth if infected; and possible gradual size change over time. The lump may be clearly visible or entirely hidden beneath the surface.
Differential Diagnosis — Lipoma vs. Other Subcutaneous Lumps
| Type | Texture | Borders | Pain | Rapid Growth | Key Distinguishing Feature | Action |
|---|---|---|---|---|---|---|
| Benign lipoma | Soft, rubbery | Well-defined | Rarely | No — slow | Mobile beneath skin — soft | Observation or excision |
| Inflamed lipoma | Tense, warm | Poorly defined | Painful | Relatively | Redness + warmth + tenderness | Anti-inflammatory ± drainage |
| Abscess | Fluctuant, tender | Ill-defined | Severe | Yes — days | Fever + discharge + intense redness | Antibiotics + surgical drainage |
| Ganglion cyst | Firm — fluid-filled | Well-defined | Intermittent | No | Near joints/tendons — transilluminates | Excision or aspiration |
| Liposarcoma | Firm or soft — deep | Ill-defined — fixed | Variable | Yes — weeks | Deep in thigh/leg — > 5 cm — non-mobile | MRI + biopsy + surgery |
| * Differential diagnosis of soft-tissue tumours requires clinical examination and appropriate imaging in all cases. Source: Mayo Clinic, AAOS Soft Tissue Tumors, RadioGraphics 2006 and 2007. | ||||||
⚠ Golden Rule: Any subcutaneous lump combining size > 3 cm + depth + non-mobility + rapid growth must be evaluated by an orthopaedic oncologist immediately — before any attempt at removal by any method.
Frequently Asked Questions
What does a typical lipoma look and feel like under the skin?
A benign subcutaneous lipoma presents distinct visual and tactile characteristics:
- Visual Profile: Typically appears as a smooth, rounded, or gently domed bulge under the skin surface.
- Texture & Consistency: Feels soft, doughy, or rubbery upon palpation, often with subtle internal lobulations.
- Mobility: Freely mobile; it easily slips and glides beneath the examining fingers when gently pushed.
- Overlying Skin: The skin above the mass looks completely normal, maintaining its usual pigment, warmth, and flexibility without redness or dimpling.
What is the ‘slippage sign’ of a lipoma?
The slippage sign is a hallmark physical examination test used by physicians:
- How It Works: When light lateral pressure is applied to the edge of the mass with an examining finger, a lipoma will slide or squirt out from underneath the fingertip into the adjacent subcutaneous space.
- Diagnostic Value: This finding confirms that the mass is well-encapsulated within the hypodermis and is not tethered or infiltrating underlying deep muscle fascia or bone.
How does the appearance of a lipoma differ from an epidermoid (sebaceous) cyst?
While both are common benign lumps, clinical examination reveals key differences:
- Lipoma:
• Depth: Located in the deeper subcutaneous fat layer.
• Texture: Soft, doughy, lobulated, and mobile under the skin.
• Surface: Smooth, normal skin with no central pore or opening. - Epidermoid (Sebaceous) Cyst:
• Depth: Attached to the dermis (superficial skin layer).
• Texture: Firmer, tense, and dome-shaped; moves directly with the skin.
• Surface: Often features a visible central dark dot or plug (punctum) through which thick, foul-smelling keratin may occasionally express.
What are the common anatomical locations where lipomas appear?
Lipomas can form wherever adipocytes reside, but they most frequently occur in specific regions:
- Upper Torso: The upper back, nape of the neck, and across the shoulders (scapular region).
- Extremities: The proximal upper arms, forearms, and thighs.
- Abdomen & Flanks: Subcutaneous tissues of the anterior abdominal wall.
- Deeper Variants: Less commonly, lipomas can develop beneath the deep fascia (subfascial or intramuscular lipomas), presenting as firmer, deeper masses that become less mobile during muscle contraction.
What is the typical size of a lipoma, and how fast do they grow?
Subcutaneous lipomas follow a slow, self-limiting growth pattern:
- Dimensions: Most superficial lipomas measure between 1 and 3 cm in diameter (similar to a marble or walnut) and rarely exceed 5 cm.
- Growth Rate: Expansion occurs very slowly over years. Any mass that enlarges rapidly over days or weeks suggests acute hematoma, secondary infection, or a non-lipomatous neoplasm requiring clinical evaluation.
What does a giant lipoma look like?
Giant lipomas are large benign tumors that alter regional anatomy:
- Clinical Definition: Any benign lipoma exceeding 5 cm in diameter or weighing over 50 grams is classified as a giant lipoma.
- Visual Presentation: Presents as an asymmetrical, heavy bulge that can distort clothing or hang as a pedunculated mass on a stalk.
- Imaging Requirement: Because of their size, giant lipomas require high-resolution ultrasound or contrast-enhanced MRI before surgery to establish deep fascial boundaries and rule out well-differentiated liposarcoma.
Does a lipoma cause skin discoloration, redness, or surface changes?
No, an uncomplicated lipoma does not produce surface skin changes:
- The epidermis overlying a classic lipoma is healthy, unstretched, and matching in color to surrounding skin.
- If the lump develops erythema (redness), surface heat, progressive throbbing, or purulent drainage, it represents an infected cyst, a furuncle (boil), or a subcutaneous abscess rather than a standard lipoma.
Can a lipoma look like or become a malignant tumor (liposarcoma)?
Benign lipomas do not transform into malignant liposarcomas:
- Lipomas and liposarcomas arise from distinct cellular precursors; a common lipoma remains benign throughout life.
- However, a low-grade or well-differentiated liposarcoma can visually resemble a large lipoma during early stages.
- Distinguishing Characteristics: Liposarcomas tend to be larger (>5 cm), feel firmer or rubbery-hard, sit deeper within muscle beds, and exhibit faster growth. High-resolution MRI and histology are definitive.
What does an angiolipoma look like, and how is it different from a common lipoma?
Angiolipomas represent a distinct vascular histological subtype:
- Visual Profile: Appears as small (typically 1 to 2 cm), multiple subcutaneous nodules beneath the skin, most commonly along the volar forearms of young adults.
- Pain Factor: Unlike standard lipomas, which are painless, angiolipomas are tender to touch or throb with temperature shifts due to microthrombi inside their proliferating capillary channels.
What red-flag signs should prompt an immediate medical evaluation of a fatty lump?
Seek surgical or dermatological evaluation if you observe any of the following features:
- Size Exceeding 5 cm: Warrants cross-sectional imaging (MRI or US) to confirm structural margins.
- Hard or Infiltrative Texture: A mass that feels stone-like, rigid, or tethered to underlying muscular planes rather than mobile.
- Rapid Growth: Accelerating enlargement across several weeks or months.
- Neurological Symptoms: Developing radiating pain, burning sensations, or paresthesias from peripheral nerve compression.
- Skin Changes: Overlying cutaneous tethering, ulceration, or dark venous discoloration.
References
- Mayo Clinic Staff. Lipoma – Symptoms and causes. Mayo Clinic. 2023. Available at: mayoclinic.org
- Cleveland Clinic. Lipoma: What It Is, Causes, Symptoms & Treatment. 2023. Available at: my.clevelandclinic.org
- AAOS OrthoInfo. Soft Tissue Tumors. 2023. Available at: orthoinfo.aaos.org
- Hospital for Special Surgery (HSS). Lipoma (Fatty Tumor). 2023. Available at: hss.edu
- Bancroft LW, et al. Lipomatous lesions of soft tissue — imaging features. RadioGraphics. 2006;26(5):1433–1491. DOI: 10.1148/rg.265055161
- Dei Tos AP. Liposarcomas: diagnostic pitfalls and new insights. Histopathology. 2014;64(1):38–52. DOI: 10.1111/his.12311
- Medscape. Lipoma Treatment & Management. 2024. Available at: emedicine.medscape.com
- Murphey MD, et al. Musculoskeletal MRI and soft-tissue tumours: a diagnostic approach. RadioGraphics. 2007;27(2):615–631. DOI: 10.1148/rg.272065142