
Does knee pain from a meniscal tear prevent you from enjoying daily life? Are you wondering whether you can manage this injury without always resorting to surgery? is Living with a Meniscal Tear possible? If these questions are on your mind, you are not alone.
Meniscal injury is among the most common knee problems worldwide. The good news is that the answer to “Can I live with a torn meniscus?” is yes — in a great many cases.
This guide explains how to manage the injury effectively, restore movement, and reduce knee pain through evidence-based strategies. We cover non-surgical treatment options, lifestyle adjustments, and therapeutic exercise — giving you the tools you need for an active, comfortable life.
What Is a Meniscal Tear?
Inside the knee joint sit two C-shaped cartilage pads — the medial and lateral menisci — that act as shock absorbers, distribute body weight, and protect the articular cartilage from direct friction. A tear occurs for one of two main reasons:
- Acute (traumatic) tear: Caused by a sudden twisting force on the knee; common in athletes and younger individuals.
- Degenerative tear: Develops gradually as the cartilage weakens with age, sometimes triggered by even minor movements.
The central (avascular) zone of the meniscus lacks a direct blood supply, severely limiting its capacity for spontaneous healing. Management therefore focuses on symptom control and building muscular support around the joint.
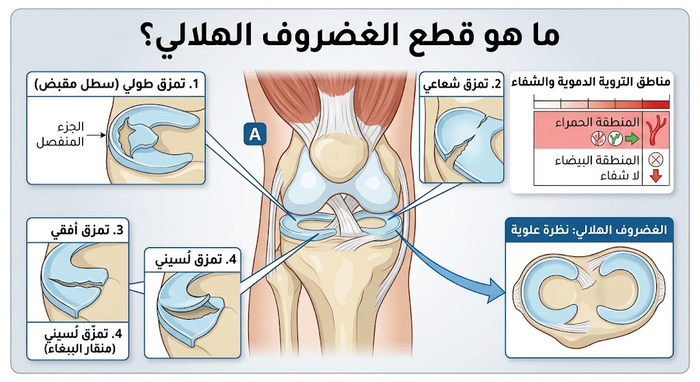
Meniscal Tear Classification by Zone and Severity
| Tear Pattern | Anatomic Zone | Blood Supply | Healing Potential | Recommended Management |
|---|---|---|---|---|
| Longitudinal – peripheral (Red Zone) | Outer 15–25% of width | Good | High | Arthroscopic repair + physiotherapy |
| Mixed (Red-White Zone) | Middle zone | Intermediate | Variable | Surgical assessment ± PRP augmentation |
| Radial / Horizontal (White Zone) | Inner (central) zone | Poor | Very low | Partial meniscectomy if conservative care fails |
| Bucket-handle | Full-width – displaced fragment | Variable | Rare | Early surgical intervention (locked knee) |
| Degenerative complex | Diffuse – associated with OA | Very poor | Negligible | Intensive conservative care ± surgery per case |
| * Based on Cooper zone classification (JBJS). Definitive management decisions require clinical examination and MRI. These categories are educational, not diagnostic. | ||||
Non-Surgical Management Strategies
Many patients ask: “Does every meniscal tear need surgery?” The answer is no. A substantial proportion of tears respond excellently to conservative care, which is your first step toward pain relief and functional recovery. Always consult a specialist in knee orthopaedics to establish the optimal treatment plan for your specific injury.
1. Pain and Inflammation Management
Initial treatment targets acute symptoms. Options include:
- NSAIDs (ibuprofen, naproxen) to reduce pain and swelling.
- Intra-articular injections: corticosteroid (acute inflammation), hyaluronic acid (joint lubrication), or platelet-rich plasma — PRP (biological healing stimulation).
2. Physiotherapy: The Cornerstone of Recovery
A structured physiotherapy programme rebuilds the muscular support system of the knee. Key exercises include:
- Quadriceps strengthening: Quadriceps sets, straight leg raises — foundational for knee stability.
- Hamstring strengthening: Prone hamstring curls to balance the muscular forces across the joint.
- Range-of-motion exercises: Gentle flexion/extension to prevent stiffness and maintain mobility.
- Proprioception / balance training: Single-leg standing, balance boards — reduces re-injury risk.
Weekly Physiotherapy Protocol — Conservative Meniscal Tear Management
| Phase | Weeks | Goals | Recommended Exercises | Permitted Activities | Restricted Activities |
|---|---|---|---|---|---|
| Acute | 1–2 | Pain/swelling control; preserve basic ROM | Quad sets, SLR, ice 20 min × 3/day, ankle pumps | Crutch-assisted walking, pool walking | Squats, stair climbing, jogging |
| Early Rehabilitation | 3–6 | Restore ROM; quad and hamstring strength | Mini-squat (0–45°), hamstring curl, wall slide, stationary bike (low resistance) | Level walking, swimming, stationary cycling | Running, jumping, deep knee bend |
| Advanced Strengthening | 7–12 | Full lower-limb strength; balance and endurance | Step-up, leg press, single-leg balance, lateral band walks | Brisk walking, swimming, flat-road cycling | Running sprints, pivoting, contact sports |
| Return to Activity | 13–16+ | Graduated return to full activity; prevention | Progressive jogging, sport-specific drills, light plyometrics | Moderate jogging, low-impact sports, full daily activities | Competitive sport without physician clearance |
| * Protocol is a general guideline. Timelines vary by tear type, patient age, and individual response. All exercises should be supervised by a qualified physiotherapist in consultation with the treating surgeon. | |||||

Lifestyle Modifications
- Avoid high-load movements: Minimise deep squatting, repetitive stair climbing, and running on hard surfaces.
- Maintain a healthy weight: Every kilogram of excess body weight places approximately four additional kilograms of force on the knee. Weight reduction is one of the most impactful modifiable factors for meniscal preservation.
- Adapt your sport: Diagnosis does not mean the end of an active life. Replace high-impact sports with knee-friendly alternatives — swimming, cycling, and walking.
When Is Arthroscopic Surgery the Answer?
Despite the effectiveness of conservative care, surgery is warranted in certain situations:
- Mechanical symptoms: Locking or inability to fully extend the knee indicates a displaced fragment obstructing the joint.
- Conservative care failure: Persistent symptoms after 6–8 weeks of intensive physiotherapy.
- High-level athletes: Those requiring a structurally sound knee for competitive return.
Conservative Care vs. Arthroscopic Surgery — Side-by-Side Comparison
| Criterion | Conservative Care | Partial Meniscectomy (Arthroscopic) | Meniscal Repair (Arthroscopic) |
|---|---|---|---|
| Ideal candidates | Partial tear, white zone, degenerative | Complete tear, white zone, failed conservative | Acute tear, red zone, young / athletic |
| Pain-relief success rate | 70–85% at 3–6 months | 80–90% short-term | 75–95% (zone-dependent) |
| OA progression risk (10 yr) | Moderate – linked to weight and adherence | Higher – tissue loss accelerates cartilage wear | Lower – tissue preserved |
| Return to desk work | 1–2 weeks | 1–3 weeks | 2–4 weeks |
| Return to sport | 3–6 months | 4–8 weeks (light activity) | 4–6 months |
| Hospital stay | None | Day surgery | 1–2 days |
| Symptom recurrence at 2 years | 30–40% without adherence | 10–20% | 5–15% (if repair heals) |
| * Figures drawn from AAOS, Mayo Clinic, and peer-reviewed comparative studies. Surgical decisions are made by the treating orthopaedic surgeon following clinical examination and MRI. | |||
⚠ Medical Disclaimer: This article is for educational purposes only and does not substitute for professional medical advice. Success rates and timelines are evidence-based estimates and may differ for individual patients.
Does a Meniscal Tear Lead to Knee Osteoarthritis?
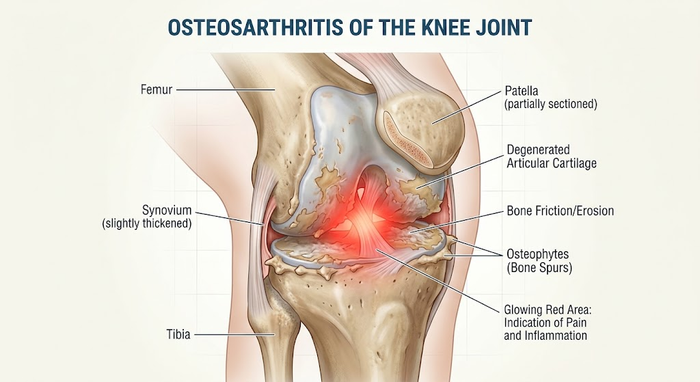
A common concern is that a tear inevitably causes arthritis. While loss of meniscal tissue does reduce shock absorption and increases friction within the joint — raising long-term osteoarthritis risk — following a structured management plan (particularly muscle strengthening and weight control) can significantly slow disease progression and preserve knee function for years.
Expert Care in Cairo, Egypt
For specialised arthroscopic knee and meniscal surgery, Dr. Ibrahim Shaarawi — consultant orthopaedic surgeon and visiting professor with local and international expertise — offers comprehensive assessment and individualised treatment planning across multiple clinic locations in Cairo.
Do not let knee pain control your life. Consult a sports-medicine orthopaedic surgeon today to establish a personalised treatment plan and begin your journey to recovery.
International References
- AAOS OrthoInfo. Meniscus Tears. American Academy of Orthopaedic Surgeons. Last reviewed 2023. Available at: orthoinfo.aaos.org
- Mayo Clinic Staff. Torn meniscus – Diagnosis and treatment. Mayo Clinic. 2024. Available at: mayoclinic.org
- Cleveland Clinic. Meniscus Tear. 2023. Available at: my.clevelandclinic.org
- Hospital for Special Surgery (HSS). Meniscus Tears: Causes, Symptoms, and Treatment Options. 2023. Available at: hss.edu
- Katz JN, et al. Surgery versus Physical Therapy for a Meniscal Tear and Osteoarthritis. New England Journal of Medicine. 2013;368(18):1675–1684. DOI: 10.1056/NEJMoa1301408
- Englund M, et al. Incidental Meniscal Findings on Knee MRI in Middle-Aged and Elderly Persons. New England Journal of Medicine. 2008;359:1108–1115. DOI: 10.1056/NEJMoa0800777
- Sihvonen R, et al. Arthroscopic Partial Meniscectomy versus Sham Surgery for a Degenerative Meniscal Tear (FIDELITY Trial). New England Journal of Medicine. 2013;369:2515–2524. DOI: 10.1056/NEJMoa1305189
- NICE Guideline NG226. Osteoarthritis in over 16s: diagnosis and management. National Institute for Health and Care Excellence. 2022. Available at: nice.org.uk