
Recurrent shoulder dislocation means the ball of the arm bone comes out of the socket more than once. It usually happens because the first dislocation tore the labrum and capsule at the front of the joint and they did not heal back in place. The risk is far higher in young people and athletes, and every new dislocation adds damage to the cartilage and the bone of the socket rim. Rehabilitation works for selected patients, but when dislocations keep recurring, arthroscopic shoulder stabilisation surgery is usually the most effective treatment.
Why does the shoulder keep dislocating?
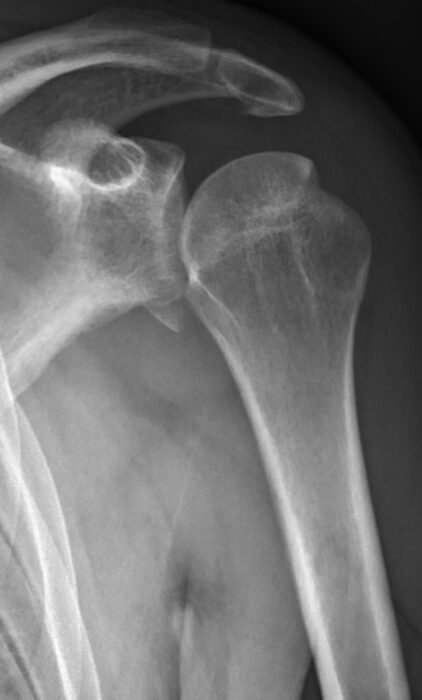
The shoulder is the body’s most mobile and least stable joint: a large ball sits on a small, shallow socket. What keeps it in place is the “bumper” formed by the labrum around the socket rim, the ligaments and capsule, and the rotator cuff muscles. In a first forward dislocation the labrum is usually torn off the front rim (a Bankart lesion), and the back of the humeral head may be dented (a Hill-Sachs defect). If these do not heal in place, the joint loses its front bumper and comes out again with less force each time.
Risk factors for recurrence
- Young age: the risk is much higher under 20–25, exceeding half in some studies of young patients.
- Contact and throwing sports: goalkeeping, handball, basketball, martial arts, swimming.
- Generalised ligament laxity.
- A large Hill-Sachs defect or bone loss at the socket rim on imaging.
- Number of previous dislocations: each one adds damage and makes the next easier.
Symptoms
- The shoulder comes out with certain movements — raising the arm out and turning it back — or even in sleep.
- A feeling that the shoulder is about to slip out (apprehension).
- Pain and weakness after each episode.
- Avoiding sport or overhead activity for fear of dislocation.
- Putting the shoulder back yourself — a sign of advanced tissue damage.
The damage from ignoring recurrent dislocation
Each dislocation grinds the front rim of the socket against the humeral head, gradually wearing the bone and enlarging the Hill-Sachs defect; in older patients the rotator cuff may tear. Over time the problem can move from a simple arthroscopic repair to needing a bone procedure such as a Latarjet, and the long-term risk of shoulder arthritis rises.
Full and partial dislocation
In a full dislocation the ball comes completely out and usually needs reduction in hospital. In a partial dislocation (subluxation) it slips out partly and returns by itself, with painful slipping and temporary weakness. Repeated subluxations are a sign of true instability and deserve the same assessment, because the damage to the labrum and capsule can be similar.
Diagnosis
- Examination: apprehension and relocation tests for anterior instability, and assessment of laxity.
- X-rays: show Hill-Sachs defects and rim fractures.
- MRI: shows the torn labrum and capsule.
- CT: measures bone loss at the socket rim and guides the choice of operation.
Treatment: without surgery or with surgery?
| Option | Usually suits | Notes |
|---|---|---|
| Physiotherapy and strengthening | Older, less active patients; a single dislocation with good stability | Does not reattach the torn labrum but improves muscle control |
| Arthroscopic Bankart | Recurrent dislocation without major bone loss | Labrum and capsule repaired with anchors and sutures |
| Bankart with remplissage | Large Hill-Sachs defect with limited bone loss | Filling the defect with posterior tendon reduces recurrence |
| Open Latarjet | Major bone loss or failed previous surgery | Rebuilds the rim with a bone block |
Treatment without surgery
A rehabilitation programme strengthens the rotator cuff and shoulder-blade muscles and improves control of shoulder position, while avoiding the positions that cause dislocation. It can work for people who avoid high-risk sport, but exercise does not put the torn labrum back, so recurrence remains common in young people. A randomised trial found that early arthroscopic stabilisation after a first dislocation in young patients reduced re-dislocation compared with a sling and rehabilitation.
Recurrent dislocation in athletes
Young athletes in contact or throwing sports are both the most likely to re-dislocate and the most affected by it, since each episode means time off. Some are therefore advised to consider stabilisation after the first dislocation, especially with a clear Bankart lesion on MRI. The decision weighs the season, sporting ambition and examination findings, with the goal of a stable shoulder that can return to play safely.
First aid when the shoulder comes out again
- Do not force the shoulder back in or let an untrained person try; it can break bone or injure nerves.
- Support the arm in a sling or scarf and apply wrapped ice.
- Go to the emergency department for X-rays before and after reduction and a nerve and circulation check.
- After reduction, book an assessment of the instability rather than just having it put back each time.
| Situation | Usual approach |
|---|---|
| Young athlete, first dislocation, Bankart lesion on MRI | Discuss early arthroscopic stabilisation |
| Young non-athlete, first dislocation | Rehabilitation and follow-up; surgery if it recurs |
| Over 40, first dislocation | Check the tendons first; a rotator cuff tear may be the bigger problem |
| Recurrent dislocation with bone loss | Usually a bone procedure such as Latarjet |
Video: is shoulder pain serious?
Frequently asked questions about recurrent shoulder dislocation
What causes recurrent shoulder dislocation?
Usually a torn labrum and capsule at the front of the joint (Bankart lesion) after the first dislocation, with or without a Hill-Sachs defect or socket bone loss.
Can recurrent dislocation be treated without surgery?
Physiotherapy may be enough for older, less active people, but it does not reattach the torn labrum, so recurrence is common in young athletes.
What damage does recurrent dislocation cause?
Wear of the socket rim, a larger Hill-Sachs defect, possible tendon tears and a higher risk of arthritis; treatment can shift from simple arthroscopy to a bone procedure.
When do I need surgery?
When dislocations recur or instability persists despite rehabilitation, or in young athletes at high risk; examination and imaging decide which operation.
How can I reduce the risk of dislocating again?
Keep up cuff and shoulder-blade strengthening, avoid forcing the raised-and-turned-back position, warm up well and do not return to play before strength and confidence recover.
To have your shoulder assessed, book a consultation, call +20 155 240 4488 or message us on WhatsApp at +20 155 554 7181.
Medically reviewed by Prof. Dr. Ibrahim Shaarawi, Professor of Orthopaedic Surgery. This article is general medical education and does not replace an examination or the plan your surgeon sets for you. See our medical disclaimer.
Related shoulder dislocation guides
Recurrent dislocation is usually treated definitively with arthroscopic shoulder stabilisation surgery. Read also:
- Arthroscopic shoulder stabilisation surgery
- Dislocated shoulder: symptoms, types and treatment
- Bankart vs Latarjet
References
- Robinson CM, et al. Functional outcome and risk of recurrent instability after primary traumatic anterior shoulder dislocation in young patients. J Bone Joint Surg Am. 2006;88(11):2326-36.
- Hovelius L, et al. Nonoperative treatment of primary anterior shoulder dislocation in patients forty years of age and younger. J Bone Joint Surg Am. 2008;90(5):945-52.
- Kirkley A, et al. Prospective randomized clinical trial comparing the effectiveness of immediate arthroscopic stabilization versus immobilization and rehabilitation in first traumatic anterior dislocations of the shoulder. Arthroscopy. 1999;15(5):507-14.
- American Academy of Orthopaedic Surgeons (OrthoInfo). Chronic Shoulder Instability.